
VBAC Calculator: See Your Estimated VBAC Success Rate
A VBAC Calculator estimates the chance of a successful vaginal birth after cesarean (VBAC) if a trial of labor after cesarean (TOLAC) is undertaken. This calculator uses the published 2021 MFMU race-neutral antenatal model. It uses maternal age, height, pre-pregnancy weight, whether the previous C-section was for an arrest disorder, vaginal-birth history, and medication-treated chronic hypertension.
The percentage is an estimate, not a guarantee or a decision about whether TOLAC is appropriate for you. Your uterine scar, current pregnancy, birth setting, medical history, and preferences still need clinical review. ACOG states that a VBAC calculator score should not be used as a barrier to TOLAC.
Enter your details to see your estimated VBAC probability. The calculator also shows which answers were used in the equation, whether the original model closely fits your situation, and useful questions to discuss with your obstetrician, midwife, or maternity care team.
Quick Facts
- Uses the published 2021 MFMU race-neutral antenatal VBAC model.
- Uses maternal age, height, pre-pregnancy weight, prior C-section indication, vaginal-birth history, and medication-treated chronic hypertension.
- Does not use race or ethnicity, BMI, induction, or a point-based scoring system.
- The original model was developed for pregnancies at 37 weeks or later with one baby in a head-down position and one prior low-transverse C-section.
- Supports metric and imperial measurements and converts them before applying the equation.
- Shows an estimated VBAC probability, model-fit context, and questions to discuss with your maternity care team. It is not a TOLAC eligibility test.
- Updated Oct 3, 2026
- Reviewed by 100Calc Research Team
MFMU 2021 race-neutral antenatal model
VBAC Calculator (Vaginal Birth After Cesarean)
Use this VBAC calculator to estimate the chance of a successful vaginal birth after a previous C-section (caesarean) if you undertake a trial of labor after cesarean (TOLAC). It uses the published 2021 MFMU model and does not use race, ethnicity, BMI, induction, or a point-based score.
MFMU 2021 antenatal estimate
Your estimated chance of a successful VBAC
Your result will appear here.
Your answers used in this calculation
These are the six factors entered into the 2021 MFMU equation.
What this estimate does not tell you
The percentage predicts VBAC success if TOLAC is undertaken. It does not calculate:
- Whether TOLAC is medically appropriate for you.
- Your individual risk of uterine rupture or other complications.
- An induction-adjusted VBAC percentage.
- The effect of current-pregnancy factors or your hospital's resources.
How to read your estimated VBAC chance
A predicted percentage should not be used by itself as a reason to deny or approve TOLAC. Your preferences, current pregnancy, prior operative records, and birth setting still matter.
Questions to discuss with your OB-GYN, midwife, or maternity team
References and model details
This implementation follows the published 2021 MFMU race-neutral antenatal equation. Small differences from another implementation can occur because the published regression coefficients are rounded.
Explore More Calculators
Use this fetal growth calculator to check baby weight percentile from ultrasound data in grams, kg, or cm and see what the result means…
Try calculatorEnter gestational sac measurements in mm or cm to calculate mean sac diameter, estimate early gestational age, compare week-by-week milestones, and see when follow-up…
Try calculatorMissed a birth control pill? Check pregnancy risk, protection status, backup contraception needs, and what to do next with our missed pill calculator.
Try calculatorUse our Pregnancy Chance Calculator to estimate your odds. Enter your cycle day, age, and method. Find out if you are in the high-risk…
Try calculatorUse our pregnancy due date calculator to find your exact Baby Due date. IVF, conception, ovulation, and ultrasound methods with weeks and timeline.
Try calculatorUse this Pregnancy Risk Calculator to check age, BMI, health history, bleeding, and twins. See if closer prenatal monitoring may be worth asking about.
Try calculator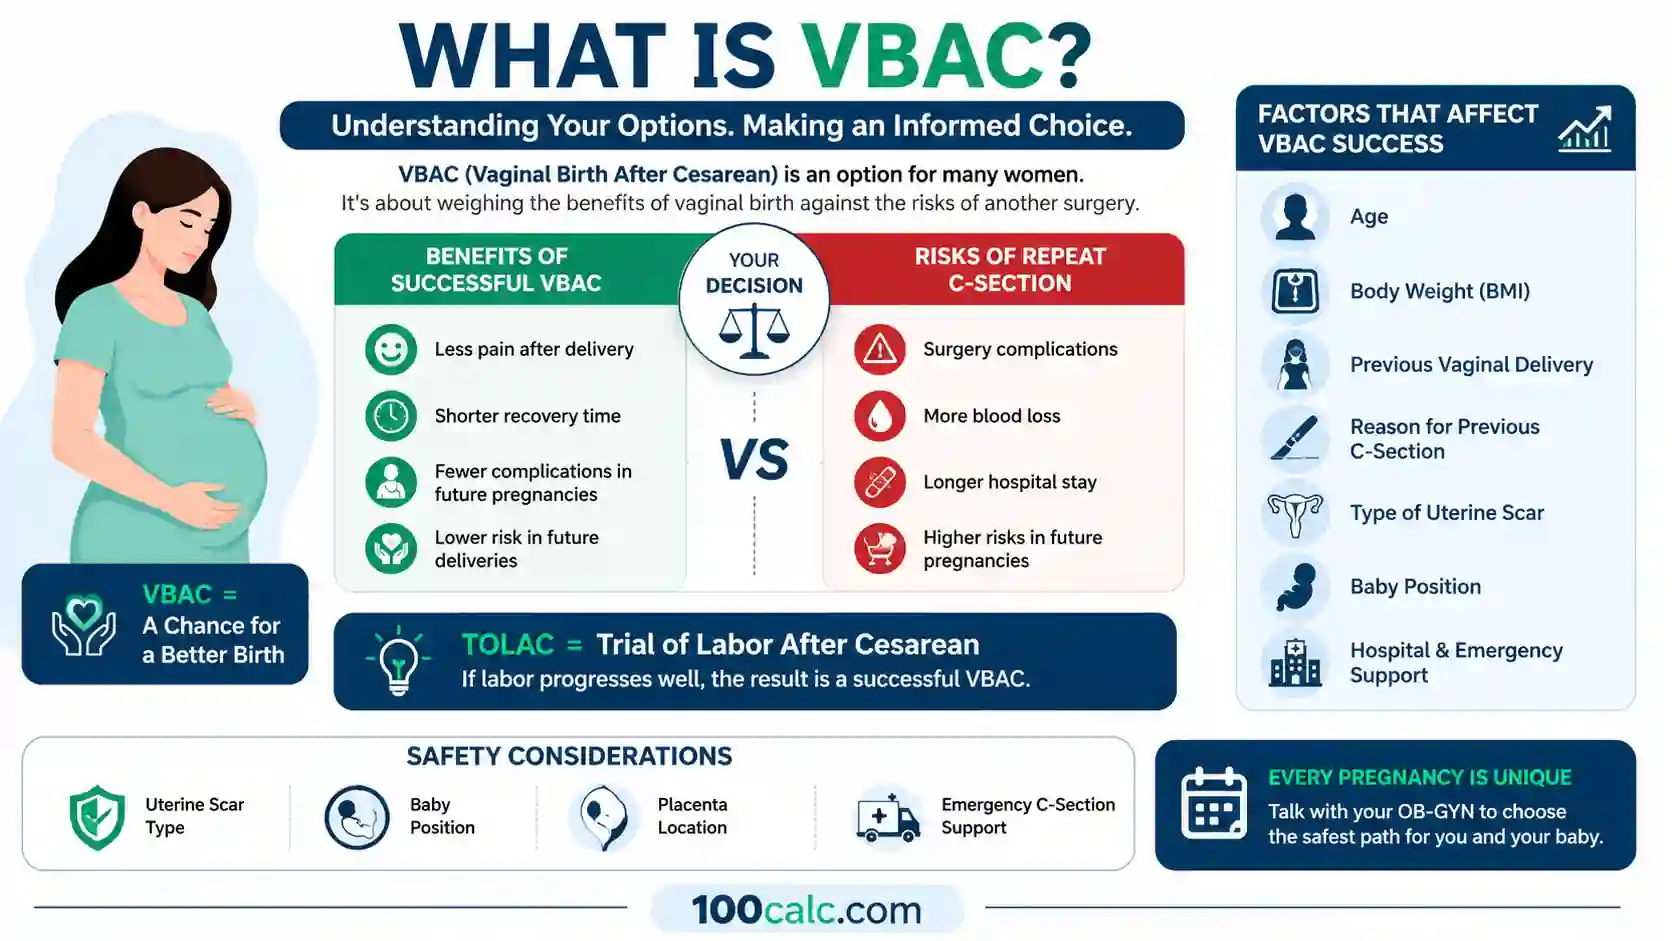
What Is Vaginal Birth After Cesarean?
VBAC gives some women a chance to avoid another surgery. A successful vaginal birth often means less pain, a shorter recovery, and fewer complications in future pregnancies. Not everyone has the same chance of success. Factors such as previous vaginal delivery, maternal age, body weight, and the reason for the earlier C-section all play a role.
Doctors usually call the attempt a TOLAC, which stands for Trial of Labor After Cesarean. If labor progresses well, the result is a successful VBAC. A woman who had a C-section because of a breech baby in her first pregnancy may have a higher chance of vaginal birth in her second pregnancy because the reason for surgery may not happen again.
Hospitals also consider safety. The type of uterine scar, baby position, placenta location, and emergency C-section support matter. These factors help doctors decide whether VBAC is a reasonable option.
What Your VBAC Estimate Means
Your VBAC estimate shows the predicted likelihood of vaginal birth if a trial of labor after cesarean (TOLAC) is attempted. The percentage is a prediction, not a guarantee, medical clearance, or eligibility decision.
ACOG recommends using a VBAC calculator as one part of shared decision-making together with your pregnancy history, uterine scar type, current clinical factors, delivery setting, and personal preferences.
Understanding Your Result
The percentage shows the model’s estimated chance of successful VBAC if TOLAC is attempted. It should not be read as a pass-or-fail score.
ACOG notes that the race-neutral prediction model tends to be better calibrated when the predicted likelihood is 60% or higher. Estimates around 40% or lower may be less accurate. Most importantly, no percentage should be used by itself to decide whether someone can or cannot attempt TOLAC.
How Should You Interpret Your VBAC Percentage?
60% or Higher
The race-neutral VBAC model has generally shown better calibration in this range. A result here still does not guarantee VBAC or automatically mean TOLAC is recommended.
41% to 59%
Treat this as an estimate that needs clinical context. Your previous C-section, uterine scar, current pregnancy, delivery setting, and preferences may affect the decision in ways the percentage cannot fully capture.
40% or Lower
Lower predicted probabilities need extra caution when interpreting the result. ACOG notes that estimates around 40% or below can differ more from observed outcomes. A low calculator result should not be used by itself to rule out TOLAC.

What You Should Do Next
Talk with your OB-GYN or maternal-fetal medicine specialist.
Ask whether spontaneous labor is likely in your situation.
Discuss induction plans and how they may affect success.
Confirm that your hospital can perform emergency C-sections if needed.
Quick Example to Test
A 33-year-old woman is 170 cm tall and had a pre-pregnancy weight of 72 kg. She has one previous low-transverse C-section. The previous C-section was for another reason, not arrest of dilation or descent. She has had a previous successful VBAC and is not being treated with medication for chronic hypertension.
Estimated VBAC probability: approximately 95.0%
Interpretation: The published 2021 MFMU model gives this profile a high estimated probability of successful VBAC if TOLAC is undertaken. A previous successful VBAC is a strong positive predictor in the equation. The result is still a prediction, not a guarantee or a decision about whether TOLAC is appropriate.
Scar type, the current pregnancy, birth setting, and other clinical factors still need review with the maternity care team.
How to Use the VBAC Calculator
The VBAC Calculator estimates your chance of a successful vaginal birth after cesarean if TOLAC is attempted. Start by checking whether the MFMU model fits your C-section history, then enter the maternal and birth-history details used in the published 2021 equation. The result shows your estimated VBAC probability, model-fit context, and the answers used in the calculation.
Check Your Previous C-Section History
Choose how many previous C-sections you have had and, if known, the type of uterine incision from your previous C-section. These answers do not change the published MFMU equation, but they help show whether the original model closely matches your situation.
Enter Your Age, Height, and Pre-Pregnancy Weight
Enter your maternal age, height, and pre-pregnancy weight. You can use metric or imperial units. The calculator converts the measurements when needed and uses age, height, and pre-pregnancy weight directly in the 2021 MFMU equation.
Add Your Previous C-Section and Vaginal-Birth History
Select whether the previous C-section was for an arrest disorder, such as arrest of dilation or descent. Then choose the vaginal-birth history that best describes you: no previous vaginal delivery, vaginal delivery before the prior C-section, or a previous successful VBAC.
Enter Your Chronic Hypertension Status
Choose whether you are being treated with medication for chronic hypertension. The published 2021 model specifically uses medication-treated chronic hypertension as an input. Pregnancy-related hypertension alone is not the same variable.
Calculate and Review Your VBAC Estimate
Select Calculate VBAC Probability to see your estimated chance of successful VBAC if TOLAC is attempted. Review the percentage, how well the model fits your history, the answers used in the calculation, important limitations, and questions you may want to discuss with your maternity care team.
Quick Example to Test
Inputs
- Age: 33 years
- Height: 170 cm
- Pre-pregnancy Weight: 72 kg
- Previous C-sections: 1
- Known uterine incision: Low-transverse
- Previous C-section indication: Another reason, not arrest of dilation or descent
- Vaginal-birth history: Previous successful VBAC
- Medication-treated chronic hypertension: No
Result
- Estimated VBAC Probability: approximately 95.0%
What This Means
A previous successful VBAC has a strong positive effect in the published MFMU equation. Age, height, pre-pregnancy weight, previous C-section indication, vaginal-birth history, and medication-treated chronic hypertension are combined to produce the estimate.
The 95.0% result is not a maximum score or a “candidate” classification. It is the model’s estimated probability of successful VBAC if TOLAC is undertaken. Whether TOLAC is appropriate still depends on clinical factors that the calculator does not determine.
How the VBAC Calculator System Works
This VBAC Calculator uses the published 2021 MFMU race-neutral antenatal prediction equation. It combines maternal age, pre-pregnancy weight, height, previous C-section indication, vaginal-birth history, and medication-treated chronic hypertension to estimate the probability of successful VBAC if TOLAC is undertaken. The calculator uses the published equation directly rather than a point-based score, BMI adjustment, or induction penalty.
Key Features & Benefits
- Uses the published 2021 MFMU race-neutral antenatal VBAC equation.
- Supports metric and imperial units and converts measurements before applying the equation.
- Shows whether your C-section history closely matches the population for which the original model was developed.
- Explains which answers were used in the probability calculation and which important clinical factors are not included in the equation.
- Provides an estimated VBAC probability with interpretation notes and questions to discuss with your obstetric or maternity care team.
Technical Process
Input Analysis
The calculator checks the entered age, height, pre-pregnancy weight, previous C-section indication, vaginal-birth history, and medication-treated chronic hypertension. Height and weight are converted to the units required by the published equation when needed.
Published Equation
The validated inputs are entered into the published 2021 MFMU logistic-regression equation. Each model variable uses its published coefficient, and the resulting value is converted into an estimated probability of successful VBAC.
Probability Output
The calculator shows the estimated VBAC probability together with model-fit context, the answers used in the equation, important limitations, and discussion points for your maternity care team. It does not classify you as a good or poor VBAC candidate.
How the VBAC Formula Works (Complete Breakdown)
The VBAC Calculator uses the published 2021 MFMU race-neutral antenatal prediction equation developed by Grobman and colleagues. Instead of starting with a fixed score and adding or subtracting points, it uses logistic regression to combine maternal age, pre-pregnancy weight, height, whether the previous C-section was for an arrest disorder, including arrest of dilation, arrest of descent, or failed induction, vaginal-birth history, and medication-treated chronic hypertension.
Race and ethnicity are not used. The result estimates the probability of a successful vaginal birth after cesarean if a trial of labor after cesarean (TOLAC) is undertaken. It does not determine whether TOLAC is medically appropriate or calculate uterine-rupture risk.
MFMU 2021 VBAC Probability Formula
					Predicted VBAC Probability (%) =
[exp(w) / (1 + exp(w))] × 100

where:

w = -5.952
    - (0.023 × Age in years)
    - (0.024 × Pre-pregnancy Weight in kg)
    + (0.056 × Height in cm)
    - (0.597 × Arrest Indication)
    + (0.868 × Vaginal Delivery Before Prior C-Section Only)
    + (1.869 × Previous VBAC)
    - (0.966 × Medication-Treated Chronic Hypertension)

Binary variables are coded as 0 or 1:

Arrest Indication
1 = previous C-section was for arrest of dilation, arrest of descent, or failed induction
0 = another indication

Vaginal Delivery Before Prior C-Section Only
1 = vaginal delivery occurred before the prior C-section, with no prior VBAC
0 = otherwise

Previous VBAC
1 = previous successful VBAC
0 = no previous VBAC

Medication-Treated Chronic Hypertension
1 = yes
0 = no
How the Formula Works
The equation first calculates a value called w, which represents the combined effect of the variables in the prediction model. That value is then converted into a probability using the logistic formula exp(w) / [1 + exp(w)]. The result is shown as an estimated percentage probability of successful VBAC if TOLAC is undertaken.
There is no fixed 65% starting score, additive point system, induction penalty, or 10% to 95% score cap in the published equation. Age, pre-pregnancy weight, height, prior C-section indication, vaginal-birth history, and medication-treated chronic hypertension enter the equation directly. Small differences from other implementations may occur because the published coefficients are rounded.
Model source: This calculator follows the published 2021 MFMU race-neutral antenatal VBAC model described by Grobman et al. and discussed in the ACOG Practice Advisory on VBAC calculators.
Understanding the Formula Variables
Age
Maternal age is entered directly into the equation in years. Its coefficient is −0.023, so increasing age lowers the predicted probability gradually when the other variables remain the same. The model does not apply a separate five-point penalty at age 35 or another fixed age cutoff.
Pre-Pregnancy Weight and Height
The 2021 MFMU equation does not use BMI as an input. It uses pre-pregnancy weight in kilograms and height in centimeters as separate variables. Weight has a coefficient of −0.024 per kilogram, while height has a coefficient of +0.056 per centimeter. The calculator can accept pounds and inches for convenience, then converts them before applying the equation.
Previous Vaginal Birth
Vaginal-birth history is handled using specific categories in the published model. If a vaginal delivery occurred only before the previous C-section and there has not been a VBAC, the equation uses the +0.868 coefficient. If there has been a previous successful VBAC, the separate prior-VBAC variable is used instead.
Previous VBAC
A previous successful VBAC is represented by a +1.869 coefficient in the published equation. It is the strongest positive obstetric-history coefficient in this model, but it remains a predictor rather than a guarantee of another successful VBAC.
Chronic Hypertension
The 2021 race-neutral model specifically uses medication-treated chronic hypertension. It is coded as 1 when present and 0 when absent, with a coefficient of −0.966. Pregnancy-related hypertension alone is not the same model input.
Factors Not Included in the Equation
Induction or spontaneous labor is not an input in this 2021 antenatal equation, so the calculator does not subtract a fixed number of percentage points for induction. Number of previous C-sections, uterine-scar type, fetal presentation, placental location, cervical findings, and local hospital resources also do not directly change the published probability equation.
Some of these factors remain clinically important and are used by this calculator to provide model-fit warnings or discussion context rather than to alter the percentage.
Previous C-Section Reason
The published model asks whether an arrest disorder was the indication for the previous C-section. This includes arrest of dilation, arrest of descent, and indications coded as failed induction. The variable is coded as 1 when an arrest disorder was present and 0 when the previous C-section had another indication. The equation applies a −0.597 coefficient when an arrest indication is present.
Other reasons, such as breech presentation or fetal concerns, are treated as “not arrest.” They do not receive a separate bonus or point adjustment.
Another Example Calculation (Step-by-Step)
This example shows how the published MFMU 2021 equation converts maternal and obstetric characteristics into an estimated VBAC probability. Each model variable is entered directly into the logistic-regression equation.
Given:
- Age = 33 years
- Height = 170 cm
- Pre-pregnancy weight = 72 kg
- Previous C-section indication = Fetal distress, not arrest of dilation/descent
- Obstetric history = Previous successful VBAC
- Medication-treated chronic hypertension = No
Calculation:
					Age = 33
Weight = 72 kg
Height = 170 cm
Arrest Indication = 0
Vaginal Delivery Before Prior C-Section Only = 0
Previous VBAC = 1
Medication-Treated Chronic Hypertension = 0

w = -5.952
    - (0.023 × 33)
    - (0.024 × 72)
    + (0.056 × 170)
    - (0.597 × 0)
    + (0.868 × 0)
    + (1.869 × 1)
    - (0.966 × 0)

w = 2.950

VBAC Probability =
[exp(2.950) / (1 + exp(2.950))] × 100

VBAC Probability ≈ 95.0%
Result:
Estimated VBAC Probability: approximately 95.0%
Meaning:
The previous successful VBAC contributes strongly to this estimate, while the previous C-section was not for an arrest disorder and medication-treated chronic hypertension is absent. The result is an estimated probability, not a guarantee of vaginal birth or a decision about whether TOLAC is medically appropriate. Induction is not part of this antenatal equation, so no fixed induction penalty is subtracted from the result.
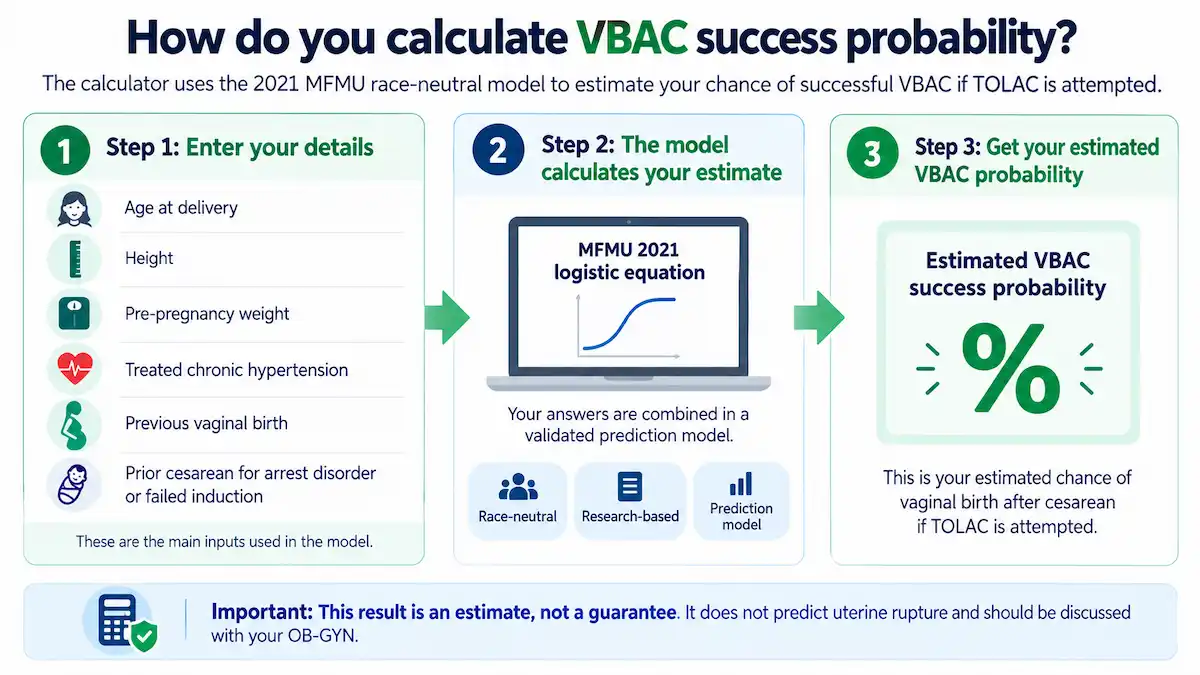
How do you calculate VBAC success probability?
A VBAC success probability is calculated with the published 2021 MFMU logistic-regression equation. The model uses maternal age, pre-pregnancy weight, height, whether the previous C-section was for arrest of dilation or descent, vaginal-birth history, and medication-treated chronic hypertension. These values are combined mathematically and converted into an estimated percentage probability of successful VBAC if TOLAC is undertaken. The model does not use a 65% starting score, BMI categories, an induction penalty, or a fixed 10% to 95% score range.
Can I have a high VBAC success rate with one previous C-section?
This example shows how the published equation handles a history of one previous C-section and a previous vaginal delivery.
Input
- Age: 29 years
- Height: 168 cm
- Pre-pregnancy weight: 64 kg
- Previous C-sections: 1
- Previous C-section indication: Breech presentation, not arrest of dilation or descent
- Vaginal-birth history: Vaginal delivery before the previous C-section, with no previous VBAC
- Medication-treated chronic hypertension: No
Result
- Estimated VBAC Probability: approximately 89.3%
Meaning
The model gives this profile a relatively high estimated probability. A previous vaginal delivery contributes positively to the equation, while the previous C-section was not for arrest of dilation or descent. The result is an estimate of VBAC success if TOLAC is undertaken, not a guarantee or an eligibility decision.
What if I have two previous C-sections?
The original 2021 MFMU model was developed primarily for people with one previous low-transverse C-section. The calculator can still show an estimate when two previous C-sections are entered, but it also gives a model-fit warning because this situation falls outside the original development population.
Input
- Age: 39 years
- Height: 160 cm
- Pre-pregnancy weight: 92 kg
- Previous C-sections: 2
- Previous C-section indication: Arrest of dilation
- Vaginal-birth history: No previous vaginal delivery
- Medication-treated chronic hypertension: Yes
Result
- Estimated VBAC Probability: approximately 16.0%
Meaning
Older maternal age, greater pre-pregnancy weight, an arrest indication for the previous C-section, no previous vaginal delivery, and medication-treated chronic hypertension all lower the model estimate. However, this percentage should be interpreted cautiously because the original model was developed for one prior C-section. Whether TOLAC is appropriate after two previous C-sections requires individual clinical review.
Does a previous VBAC improve future VBAC chances?
Yes. A previous successful VBAC is one of the strongest positive predictors in the published 2021 MFMU equation.
Input
- Age: 31 years
- Height: 165 cm
- Pre-pregnancy weight: 61 kg
- Previous C-sections: 1
- Previous C-section indication: Fetal distress, not arrest of dilation or descent
- Vaginal-birth history: Previous successful VBAC
- Medication-treated chronic hypertension: No
Result
- Estimated VBAC Probability: approximately 95.2%
Meaning
A previous successful VBAC has a strong positive coefficient in the equation and substantially increases the estimated probability in this example. The 95.2% result is produced by the logistic-regression equation; it is not a score cap or a “very favorable candidate” category.
Can women over 35 still have a high estimated VBAC probability?
Yes. Maternal age is one factor in the prediction equation, but there is no separate age-35 cutoff or fixed five-point penalty.
Input
- Age: 37 years
- Height: 170 cm
- Pre-pregnancy weight: 70 kg
- Previous C-sections: 1
- Previous C-section indication: Placenta previa, not arrest of dilation or descent
- Vaginal-birth history: Vaginal delivery before the previous C-section, with no previous VBAC
- Medication-treated chronic hypertension: No
Result
- Estimated VBAC Probability: approximately 87.0%
Meaning
Age enters the equation continuously, so the model does not suddenly subtract points when someone turns 35. In this example, the previous vaginal delivery and other entered characteristics still produce a relatively high estimated probability.
Quick Rules to Remember
A VBAC probability is an estimate, not a guarantee or an eligibility decision. The 2021 MFMU equation uses age, height, pre-pregnancy weight, previous C-section indication, vaginal-birth history, and medication-treated chronic hypertension. A previous VBAC is a strong positive predictor. Race, ethnicity, BMI, induction, and a point-based score are not inputs in this antenatal equation. Review your percentage together with your uterine scar, current pregnancy, birth setting, and personal preferences with your maternity care team.
VBAC Calculator Result Benchmarks Explained
Your VBAC percentage is the model’s estimated chance of successful vaginal birth if TOLAC is undertaken. It is not a pass/fail score or a medical eligibility cutoff. ACOG notes that predictions tend to be more accurate at 60% or higher, while estimates of 40% or lower can be less precise. The result should be reviewed together with your pregnancy history, current pregnancy, birth setting, and personal preferences.
| Estimated VBAC Probability | How to Read It | What to Keep in Mind |
|---|---|---|
| 60% or Higher | Higher predicted probability. The model tends to be better calibrated in this range. | This is still an estimate. It does not guarantee VBAC or determine whether TOLAC is appropriate for you. |
| 41% to 59% | The estimate falls in the middle predicted range and needs individual clinical context. | The percentage alone cannot determine whether TOLAC or a planned repeat C-section is the better option for you. |
| 40% or Lower | Lower predicted probability. Estimates in this range can be less accurate. | A low estimate should not be used by itself to rule out TOLAC. |
Important: A VBAC calculator estimates the likelihood of successful vaginal birth if TOLAC is attempted. It does not determine medical eligibility. Review your result with your maternity care team together with your uterine scar, previous birth history, current pregnancy, birth setting, and personal preferences.
Interpretation
A higher percentage means the model predicts a greater likelihood of successful VBAC, but no percentage guarantees the outcome. Lower estimates may also carry greater prediction uncertainty. ACOG advises that a VBAC calculator result should not be used as a barrier to TOLAC, so the estimate should be considered together with the full clinical picture and the patient’s preferences.
Pro Tip
Use your VBAC estimate as a starting point for discussion, not as a stand-alone decision. Ask your maternity care team to review your uterine scar, previous birth history, current pregnancy, planned birth setting, and any labor or induction plans that are not included in this calculator.
What to Discuss After You Get Your VBAC Estimate
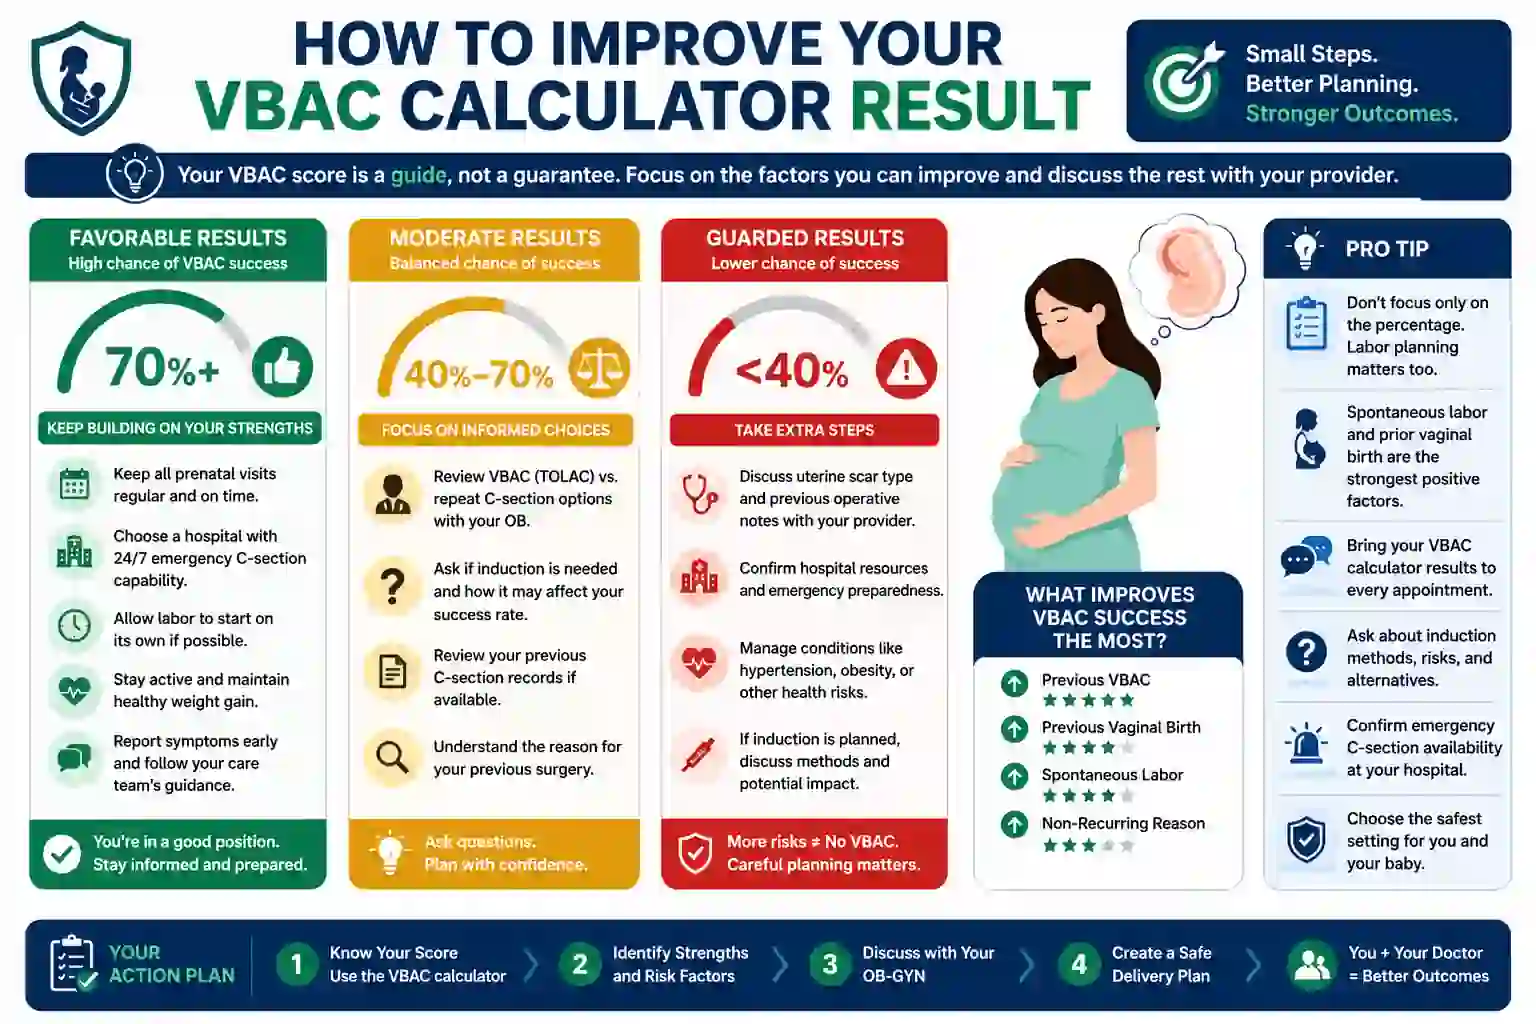
Your VBAC estimate is only one part of the decision. Use the percentage to start a discussion about your previous C-section, uterine scar, prior vaginal births, current pregnancy, hospital resources, and your own birth preferences. Your maternity care team can also explain factors that are important clinically but are not included in this calculator.
If Your Estimate Is 60% or Higher
A result of 60% or higher is a higher predicted probability, and estimates in this range tend to be better calibrated. Ask whether your uterine incision, previous birth history, current pregnancy, and planned birth setting support TOLAC in your situation. Also ask what monitoring and emergency support would be available during labor.
If Your Estimate Is 41% to 59%
A result between 41% and 59% needs more context than the percentage alone can provide. Ask how your previous C-section history, uterine scar, prior vaginal births, current pregnancy, and local hospital resources affect the decision between TOLAC and a planned repeat C-section. If induction may be considered later, ask how it could affect your labor plan and clinical risks.
If Your Estimate Is 40% or Lower
A result of 40% or lower is a lower model estimate, but it should not automatically rule out TOLAC. Lower predicted values can be less accurate, and the calculator cannot assess every factor that matters for birth planning. Ask your maternity care team to review your uterine scar, previous C-section history, current pregnancy, personal goals, and the resources available where you plan to give birth.
Pro Tip
Bring your calculator result to your next maternity appointment, but also bring your previous C-section records if you have them. The percentage is most useful when your care team can review it together with your uterine incision, previous birth history, current pregnancy, and available hospital support.
You Might Also Find These Helpful
Pregnancy & Fertility 44
One Time Pregnancy Calculator estimates pregnancy odds from one encounter, plus fertile window timing, test date, due date, and 21-day testing guidance.
Try calculatorUse the AMH Calculator to convert ng/mL or pmol/L, compare your result with age-based data, and see what it may mean for IVF, fertility,…
Try calculatorUse the Baby Eye Color Calculator with parents, grandparents, or sibling context to compare Brown, Green/Hazel, and Blue/Grey model estimates instantly.
Try calculatorBasal Body Temperature Calculator checks reading conditions and analyzes your temperature pattern for a sustained shift that may be consistent with ovulation.
Try calculatorBPD gestational age calculator: estimate fetal age from BPD, compare your week, check normal BPD ranges, and understand ahead or behind results.
Try calculatorCalculate odds with the Chance of Twins Calculator. Enter maternal age and history. Find your probability instantly. See if you will conceive multiples now.
Try calculatorFind out exactly when you conceived. Our free Conception Calculator uses your Due Date, LMP, or Ultrasound to estimate your fertilization date and fertile…
Try calculatorUse our Conception Date Due Date Calculator to find your baby's arrival date. Enter your conception or intercourse date for clinical 40-week results.
Try calculatorContraceptive effectiveness calculator to compare birth control methods, typical vs perfect use, backup protection, and 5-year pregnancy risk.
Try calculatorUse this CRL calculator to estimate gestational age and due date from crown-rump length in mm or cm. Compare CRL, LMP, and IVF dating…
Try calculatorEstimate your monthly and 12-month pregnancy odds by age, partner age, and cycle dates. See your fertile window and when to seek fertility help.
Try calculatorUse this fundal height calculator to compare your cm measurement by week, check growth range, estimate baby weight, and know when to ask about…
Try calculatorCommon Mistakes When Using the VBAC Calculator
A VBAC calculator works best when each answer matches your medical records and pregnancy history. Common mistakes include using current weight instead of pre-pregnancy weight, confusing a previous vaginal birth with a previous VBAC, or misunderstanding which medical details are part of the prediction equation.
- Confusing a vaginal delivery before a C-section with a previous successful VBAC.
- Entering your current pregnancy weight instead of your pre-pregnancy weight.
- Confusing the uterine incision with the skin scar on your abdomen. The scar-type question refers to the incision made in the uterus during the previous C-section.
- Misreading an arrest disorder. In this model, it includes arrest of dilation, arrest of descent, and failed induction as the reason for the previous C-section.
- Treating any high blood pressure as the model input. The equation specifically uses medication-treated chronic hypertension.
- Using the estimated percentage as medical clearance, a uterine-rupture risk estimate, or a final decision about whether TOLAC is appropriate.

Frequently Asked Questions (FAQs)
How do you calculate the VBAC rate?
The 2021 MFMU VBAC model uses maternal age, height, pre-pregnancy weight, the reason for the previous C-section, vaginal-birth history, previous VBAC, and medication-treated chronic hypertension. These values are combined in a logistic-regression equation to estimate the probability of successful VBAC if TOLAC is attempted. It does not start with a fixed base score or use BMI, race, ethnicity, induction, or a point system.
What's the chance of a successful VBAC?
ACOG notes that overall VBAC rates among people who attempt TOLAC are about 60% to 80%, but an individual person’s chance can be higher or lower. Previous vaginal birth, especially a previous successful VBAC, can raise the predicted probability. Your calculator result is an estimate, not a guarantee.
Does this VBAC calculator use race or ethnicity?
No. This calculator uses the 2021 MFMU race-neutral model, which does not include race or ethnicity. ACOG discusses this updated model and advises against using race or ethnicity to reduce a person’s estimated chance of VBAC.
Does induction reduce VBAC success?
Induction can reduce the chance of successful vaginal birth compared with labor that starts on its own, and it can also affect the risks of TOLAC. However, induction is not an input in this 2021 antenatal VBAC calculator, so the calculator does not apply a fixed induction penalty. Discuss any induction plan separately with your maternity care team.
Can I have a VBAC after two C sections?
Possibly. TOLAC may be considered for some people with two previous low-transverse C-sections after individual counseling. The original 2021 MFMU calculator was developed in people with one prior C-section, but a 2024 study found that the same race-neutral model also predicted VBAC reasonably well in people with two prior C-sections. Scar type, pregnancy history, and available hospital resources still need clinical review.
How many months should I wait before trying VBAC?
There is no single waiting period that automatically makes VBAC safe or unsafe. ACOG notes that shorter intervals after a C-section are linked with higher risks during a later TOLAC. Delivery-to-delivery intervals of about 18 to 24 months or less have been associated with a higher risk of uterine rupture, while becoming pregnant less than 6 months after a birth is also linked with higher maternal risks. Discuss the timing of your next pregnancy with your maternity care team.
Does maternal age affect VBAC success?
Yes. Maternal age is one of the variables in the 2021 MFMU equation. Increasing age gradually lowers the predicted probability when the other inputs stay the same. The model does not use a special age-35 cutoff or apply a fixed penalty when someone turns 35.
How can I increase VBAC success?
No step can guarantee a successful VBAC. Previous vaginal birth, especially a previous successful VBAC, is linked with a higher chance of success. Labor that starts on its own is also associated with higher VBAC success clinically, but spontaneous labor is not an input in this 2021 antenatal calculator. The most useful step is to review your previous C-section records, current pregnancy, birth setting, and labor plan with your maternity care team.
Which factor increases VBAC success the most?
Among the obstetric-history inputs in the 2021 MFMU model, a previous successful VBAC has the strongest positive coefficient. Previous vaginal delivery before the C-section also raises the predicted probability. These factors improve the estimate, but neither guarantees another successful VBAC.
What does TOLAC mean?
TOLAC stands for Trial of Labor After Cesarean. It means attempting labor after a previous C-section with the goal of having a vaginal birth. If the trial of labor results in a vaginal delivery, that birth is called a VBAC. If TOLAC is unsuccessful, another C-section may be needed.
Does obesity affect VBAC success?
Higher BMI has been associated with lower VBAC success in broader clinical research, but BMI alone does not decide whether TOLAC is appropriate. This 2021 MFMU calculator does not use BMI as an input. It uses pre-pregnancy weight and height separately in the prediction equation.
Questions?
We had love to hear from you! Whether you are reporting an issue, suggesting a new calculator, or exploring collaboration opportunities — we are here to help. Every message helps us make 100calc smarter, faster, and more helpful for everyone.
Why People Trust 100calc
At 100calc.com, we focus on accuracy, speed, and trust. Every calculator we create is designed to give reliable, instant, and easy-to-understand results you can truly depend on.